


Uterine Cancer Treatment
Treatment options by stage
- In most cases, the main treatment for uterine cancer is surgery, and treatment at an early stage usually has better results.
- Minimally invasive surgery is suitable for many patients; the type of operation depends on how far the cancer has spread and on individual circumstances.
- The tumor type, the stage of the cancer and its molecular features determine whether radiation therapy or drug treatment is needed.
- For some patients with early, low-risk cancer, keeping the uterus (womb) and fertility may be an option to discuss.
- In the first 2 years after treatment, follow-up exams are usually every 6 months for the low-risk group and every 3 months for the high-risk group.
Video in Persian
From anywhere in the world
Tehran clinic services
What can I do while waiting for my biopsy result?
Whether you are facing this illness yourself or worried about someone you love, knowing the next step can make the road ahead feel more manageable.
Until the pathology result is ready, no firm decision about a treatment plan can be made. How long results take varies from one center to another; ask your doctor’s office or the lab how long results usually take, and write down your symptoms and questions. To prepare for your next appointment, see the section “Questions to ask your doctor about uterine cancer treatment”.
Uterine cancer vs. cervical cancer: how treatment differs
Uterine (endometrial) cancer
It starts in the lining of the uterus. For most patients, surgery is the main treatment; whether radiation therapy or drug treatment is also needed depends on the stage of the cancer, the tumor’s features and individual circumstances.
Cervical cancer
It starts in the cervix, and most cases are linked to HPV. Depending on the stage, treatment may include surgery, radiation therapy combined with chemotherapy, or drug treatments.

About this image: The highlighted part is the lining of the uterus, or endometrium: the layer that thickens during the menstrual cycle and sheds during your period. Endometrial cancer starts in this layer. The cervix is in the lower part of the uterus, and cervical cancer is different from endometrial cancer.
The uterine cancer treatment pathway
Confirming the diagnosis
A tissue sample from the uterus is examined in a pathology lab to find out whether cancer is present and what type it is. This result is the basis for decisions about treatment.
Finding the stage and grade
The grade of the tumor is found by examining the tissue. Imaging and, in many cases, the findings at surgery help determine the stage of the cancer. Molecular tests also help guide the choice of treatment.
Choosing a treatment plan
Your care team puts together the gynecologic oncologist’s opinion, your test results, the tumor’s molecular features and your circumstances, and explains the options that suit you.
Surgery
In most cases, surgery is the main part of treatment.
Additional treatment, if needed
After surgery, the pathology results and the tumor’s features show whether more treatment is needed. Depending on the situation, radiation therapy or drug treatment may be recommended; not every patient needs it.
Follow-up after treatment
Regular appointments are used to check for possible signs of the cancer coming back, side effects of treatment and how your recovery is going. How often you are seen, and which tests you need, are set according to your situation.
Which specialists treat uterine cancer?
Treatment is usually led by a gynecologic oncologist, with other specialists working together at different points along the way.
Gynecologist
First assessment and referral
- Assessing early symptoms and abnormal bleeding
- Ordering an ultrasound, basic tests and an endometrial biopsy
- Prompt referral to gynecologic oncology once the diagnosis is confirmed
Gynecologic Oncologist
Leading treatment and surgery
- Overall management of your care and treatment plan
- Specialized surgery for uterine tumors
- Accurate staging of the cancer
Medical oncologist
Drug treatments and additional therapy
- Planning drug treatment and chemotherapy
- Coordinating with a radiation oncologist (if needed)
- Managing medication side effects and follow-up during recovery
How the stage and grade of the tumor affect treatment choices
This is a general overview. The tissue type, molecular status and individual circumstances can change the treatment plan.
Stage I: Confined to the body of the uterus
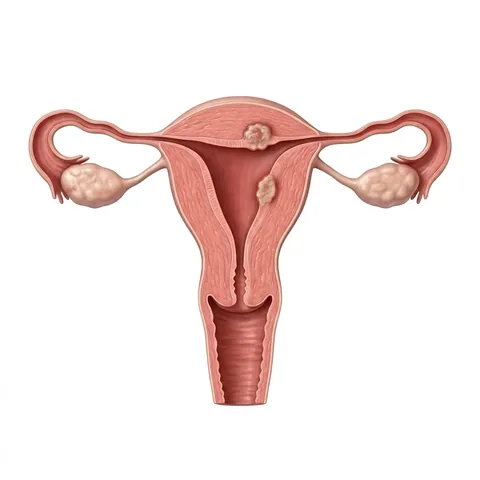
Usual treatment approach:
Usually surgery, including hysterectomy, removal of the fallopian tubes and ovaries, and assessment of the lymph nodes
Main goal of treatment:
Eliminating the cancer
Stage II: Spread to the cervix
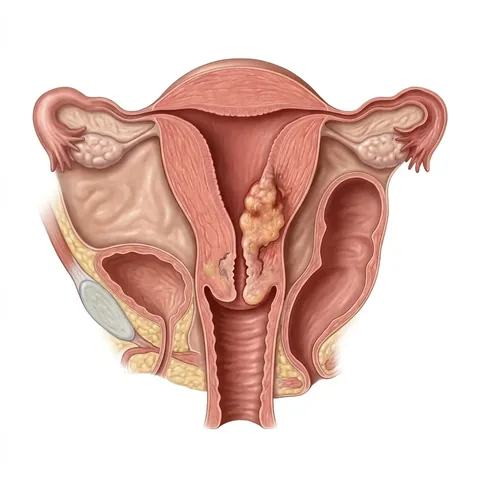
Usual treatment approach:
Surgery and, in many cases, additional radiation therapy
Main goal of treatment:
Eliminating the cancer
Stage III: Regional spread
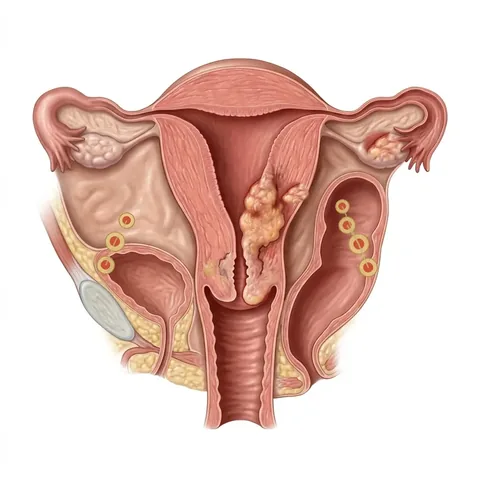
Usual treatment approach:
Surgery with chemotherapy, radiation therapy or both
Main goal of treatment:
Treating and controlling the cancer
Stage IV: Distant spread
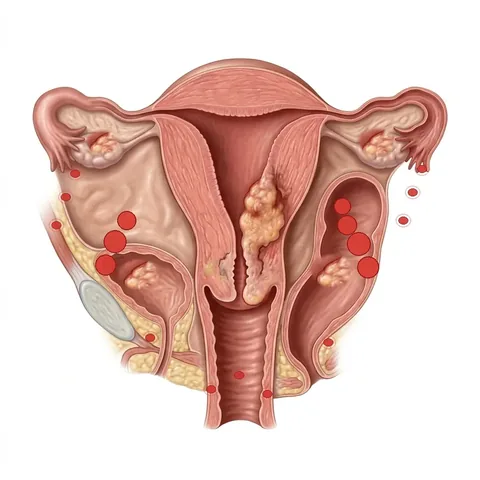
Usual treatment approach:
Chemotherapy, hormone therapy, targeted therapy or immunotherapy, often in combination, or palliative care
Main goal of treatment:
Controlling the cancer, easing symptoms and maintaining quality of life
What does tumor grade mean?
The grade shows how different the tumor cells look from normal tissue. A higher grade usually goes with more aggressive behavior.
Grade is different from stage (how far the cancer has spread), and both play a part in choosing treatment.
How is the final stage determined?
The final stage is often determined after surgery and a detailed examination of the tissue. Imaging before surgery is not always enough on its own.
Important: The tumor’s molecular features can also lower or raise the need for additional treatment.
How is uterine cancer surgery done?
For most people with endometrial cancer, surgery involves removing the uterus and cervix, which is called a “total hysterectomy.” The fallopian tubes and ovaries are usually removed as well, and the lymph nodes are assessed if needed. The type and extent of surgery depend on the tumor’s features, the stage of the cancer and your circumstances.
Types of hysterectomy and how they differ

Total hysterectomy
In this surgery, the uterus is removed together with the cervix. Removing the ovaries and assessing the lymph nodes are separate steps that may be done at the same time; whether they are needed depends on the features of the cancer and your circumstances.
Radical hysterectomy
Along with the uterus and cervix, some of the surrounding tissue and the upper part of the vagina are removed. This more extensive surgery is not the usual treatment for endometrial cancer and is considered only in special situations.
Vaginal hysterectomy
In this approach, the uterus is removed through the vagina. “Vaginal” describes the route of surgery; it says nothing about how much tissue is removed. It may be combined with laparoscopy to check inside the abdomen or the lymph nodes.
Laparoscopic or robotic surgery
The surgeon operates through a few small cuts in the abdomen. For suitable patients, these approaches usually mean a shorter hospital stay and a quicker return to daily activities than open surgery.
Is minimally invasive surgery suitable for uterine cancer?
Yes. For many people with endometrial cancer confined to the uterus, it is the preferred approach. Small incisions do not mean the surgery is incomplete; the choice of approach depends on whether the tumor can be removed safely, how far the cancer has spread and your circumstances.
Open surgery or laparoscopy?
Open surgery
Full recovery usually takes about 6 to 8 weeks
Widespread disease, a very large uterus, or when minimally invasive surgery is not suitable
A diagnosis of endometrial cancer is confirmed by examining a tissue sample in a pathology lab. In a biopsy, a small amount of the uterine lining is taken for this examination.
Larger incision; the hospital stay and recovery are usually longer.
Minimally invasive surgery
A few days to about two weeks, usually with a shorter hospital stay
Many patients with endometrial cancer confined to the uterus.
Smaller incisions and usually fewer wound complications.
Checking the lymph nodes
Checking the lymph nodes helps show how far the cancer has spread and guides the choice of treatment. In many patients, a tracer is injected to find the first lymph nodes that drain lymph fluid from the uterus, and these nodes are biopsied; they are called “sentinel lymph nodes.” This approach can reduce the need to remove many lymph nodes and lower the risk of leg swelling (lymphedema). Whether more lymph nodes need to be checked depends on the surgical findings and the sample results.
What other treatments are there for uterine cancer?
Depending on the stage of the cancer, the tumor’s features and your general health, these treatments may be used after surgery or to treat advanced cancer or cancer that has come back.
Radiation therapy
Radiation is aimed at a specific area to target the cancer cells. It may be given from outside the body (external radiation), as internal radiation therapy (brachytherapy), or as a combination of both.
Chemotherapy
Medicines are given in several cycles to kill cancer cells or stop them from growing. Many treatment plans involve about 6 cycles; the number of cycles depends on the type of plan, how the cancer responds and side effects.
Hormone therapy
In some hormone-sensitive tumors, medicines such as progestins can hold back the growth of the cancer. This approach may be considered in some cases of cancer that has come back and, with close follow-up, for selected patients who want to preserve their fertility.
Targeted therapy
These medicines target specific pathways that help the tumor grow. For example, lenvatinib combined with pembrolizumab may be chosen in some advanced or recurrent cases, based on test results and previous treatments.
Immunotherapy
It helps the immune system recognize and attack cancer cells. In some advanced or recurrent cases, it is used together with chemotherapy or on its own. The results of MMR/MSI testing (mismatch repair and microsatellite instability) and previous treatments help decide whether it is used.
Palliative care
It is offered to ease pain and other symptoms, manage the side effects of treatment and maintain quality of life. This care can start at diagnosis, alongside cancer treatment.
How do molecular tests help?
Tests such as POLE, MMR/MSI and p53 give information about the tumor’s features and the chance of the cancer coming back. Together with the stage and grade of the tumor, these results help with decisions about additional treatment and the choice of some targeted therapies or immunotherapy.
Can fertility be preserved?
For some patients, such as those with grade 1 endometrioid cancer that has not spread into the muscle of the uterus, treatment aimed at keeping the uterus and the possibility of pregnancy may be considered.
This treatment usually involves progestin tablets or a progestin-releasing IUD (intrauterine device; in the UK, a hormonal coil), sometimes combined with removing the abnormal tissue (lesion) through hysteroscopy. Regular biopsies and follow-up are essential, and once you have finished having children, removing the uterus is usually recommended.
How is uterine cancer managed during pregnancy?
Endometrial cancer diagnosed during pregnancy is very rare. The treatment plan depends on how far along the pregnancy is, the type and extent of the cancer, and your preferences. Decisions should be made without delay, together with the gynecologic oncology team and a maternal-fetal medicine specialist.
How successful is uterine cancer treatment at each stage?
These figures show how likely people with endometrial cancer are to be alive five years after diagnosis, compared with similar people who do not have this cancer. They are not the percentage of people who are cured. The figures below are based on data from patients in the United States diagnosed between 2015 and 2021.
Confined to the uterus
About 96%
Regional spread
About 72%
Distant spread
About 22%
What do these numbers mean for you?
These numbers do not decide your future and do not predict how your treatment will go. They do not mean that life expectancy is limited to five years. The type and grade of the tumor, its molecular features, your general health and how you respond to treatment also affect the outcome. These three statistical groups do not correspond exactly to stages I to IV.
Care and follow-up after uterine cancer treatment
After treatment ends, care for side effects, checks for new symptoms and regular appointments continue. These 5 steps are a guide to your care and follow-up; your exact plan is set according to the risk of the cancer coming back and your needs.
The first weeks after treatment
Possible short-term side effects
Bleeding, infection, or leg swelling (lymphedema) if lymph nodes were removed
Tiredness, and irritation of the bowel or bladder (such as burning when urinating or changes in bowel habits)
Tiredness, nausea, temporary hair loss, or numbness and tingling in the hands and feet
Weight changes, mood changes, and a possible risk of blood clots
If your ovaries were removed
Early menopause (caused by surgery)
If you had not reached menopause before treatment, removing the ovaries brings on menopause suddenly. Whether hormone replacement therapy (HRT) can be used depends on the type of tumor and the level of risk, and the decision should always rest with your treating doctor.
Years 1 and 2
Close follow-up
Each visit includes a full physical exam and a pelvic exam.
Years 3 to 5
Less frequent visits
Throughout this time
The cancer may come back in the vagina or pelvis, and sometimes in other organs.
⚠️ Tell your doctor about any new bleeding or bloody discharge, ongoing abdominal or pelvic pain, a lasting cough or unexplained weight loss. Do not wait until your next appointment to report these symptoms.
Screening suited to your age and history, such as breast and bowel (colorectal) screening, should also continue separately.
Important: The exact follow-up plan should be tailored to each person. A physical exam is the main part of follow-up, so tests or scans are ordered only when symptoms or examination findings call for them, based on your treating doctor’s judgment.
If you are a family member or caregiver
- With the patient’s permission, help write down questions, arrange appointments and keep track of treatment. Respect their decisions and preferences.
- Tell the care team about any family history of cancer. Tissue tests such as MMR/MSI, together with personal and family history, can show whether genetic counseling is needed.
Can herbal or home remedies replace medical treatment?
Some foods or herbs can replace surgery, chemotherapy or radiation therapy.
Good nutrition helps keep your body strong during treatment, but it does not replace cancer treatment. If you take supplements or herbal remedies, tell your care team so they can check for possible interactions with your medicines.
Questions to ask your doctor about uterine cancer treatment
- What are the stage and grade of my tumor?
- Have the tumor's molecular features been tested, and how do they affect my treatment?
- Which type of surgery is right for me, and why?
- Do my lymph nodes need to be checked? How?
- Do I need additional treatment?
- What is my follow-up plan?
- If my ovaries are removed, what are my options for early menopause?
Frequently asked questions about uterine cancer treatment
Is uterine cancer curable?
In many cases, especially when the cancer is found at an early stage, the chance of successful treatment is high. The exact answer depends on the stage, grade and features of the tumor.
Does a Pap smear detect uterine cancer?
No. A Pap test (Pap smear; in the UK, a smear test) checks the cervix. Uterine cancer is usually diagnosed with a transvaginal ultrasound and an endometrial biopsy.
Can the cancer come back after surgery?
Yes, the cancer can come back (recur), and the chance depends on the features of the disease. Regular follow-up is done to check for symptoms and for side effects of treatment.
Which is better: open surgery or laparoscopic (keyhole) surgery?
For many patients, minimally invasive surgery is suitable, but the size of the uterus, how far the cancer has spread and individual circumstances can make open surgery necessary.
Can young women get uterine cancer?
Yes. Endometrial cancer is seen more often after menopause, but it can also happen at younger ages. Abnormal bleeding is not necessarily a sign of cancer; even so, bleeding between periods or a lasting change in your period pattern should be checked.
Does chemotherapy cause hair loss? How many cycles are there?
Hair loss depends on the type of medicine and happens with many chemotherapy plans for endometrial cancer, but it is usually temporary. Treatment often involves about 6 cycles; the exact number is set according to the treatment plan, how your body responds and any side effects.

Your questions
No question has been published on this page yet.
Ask the first one. The answer is published right here, under your question.






Write your question